Safety profiles for minibeam radiation show significantly fewer skin injuries and hair loss compared to the side effects observed with traditional wide-field radiation techniques. This clinical advantage marks a pivotal shift in managing primary central nervous system lymphoma, a notoriously aggressive malignancy that remains confined to the brain and eyes. While current standard-of-care protocols, typically involving high-dose chemotherapy and whole-brain radiotherapy, can initially force the disease into remission, the long-term prospects for these patients are historically discouraging. Relapses occur frequently, and the sheer intensity of uniform radiation required to kill deep-seated tumor cells often inflicts permanent cognitive damage and tissue necrosis. The medical community has long sought a way to integrate advanced immunotherapies, such as Chimeric Antigen Receptor T cells, into the brain without triggering a catastrophic inflammatory response. Recent research now suggests that the secret to success lies not in the dose, but in the delivery.
The Modality Debate: Technical Innovations in Radiation Delivery
Conventional radiotherapy approaches the challenge of brain tumors with a ‘scorched earth’ philosophy, delivering a uniform field of ionizing radiation across the entire target volume. While this method is undoubtedly effective at eradicating rapidly dividing lymphoma cells, it does not discriminate between the malignant tissue and the surrounding healthy parenchyma. This lack of selectivity often leads to widespread vascular damage and fibrotic scarring, which effectively seals off the tumor site from the body’s own immune system. In the context of bridging therapy, where radiation is used to debulk a tumor before introducing immune cells, this uniform damage can be counterproductive. By destroying the delicate architecture of the brain’s microenvironment, conventional radiation may inadvertently prevent therapeutic T cells from infiltrating the site or surviving long enough to be effective. This biological barrier has historically limited the efficacy of cell-based therapies in neuro-oncology.
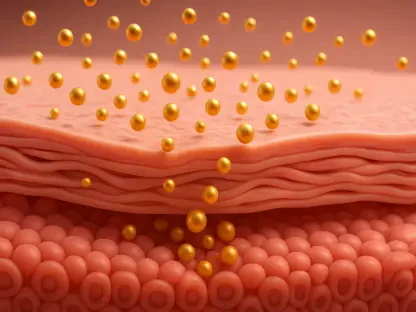
Minibeam radiation therapy, or MBRT, offers a sophisticated alternative by utilizing spatial fractionation to spare healthy tissue. Instead of a solid, uniform block of radiation, MBRT delivers the therapeutic dose through an array of narrowly collimated, parallel beams that are only 700 micrometers wide. This configuration creates a distinct ‘peak-and-valley’ dose distribution across the brain tissue. In recent preclinical evaluations, the ‘peaks’ directly hit by the beams received massive doses exceeding 80 Gy, while the ‘valleys’ between them were exposed to less than 5 Gy. This technique leverages the dose-volume effect, a biological principle where healthy tissue can withstand extremely high levels of radiation if the irradiated volume is sufficiently small. Healthy cells residing in the low-dose valleys are capable of migrating into the high-dose peak regions to facilitate rapid repair, thereby preserving the structural and functional integrity of the brain even under intense treatment.
Outcome Analysis: Experimental Models and Survival Results
To evaluate the synergy between radiation and immunotherapy, researchers utilized a specialized orthotopic rat model that closely mimics human biological responses to lymphoma. These animals were implanted with human lymphoma cells and then divided into several treatment arms to compare monotherapies against combination strategies. The control group, which received no treatment, succumbed to the disease within 18 days, while those treated with CAR T cell monotherapy saw their survival extended to 43 days. When radiation was applied alone, both conventional and minibeam methods produced similar modest gains, reaching 32 and 36 days respectively. These baseline figures established a clear benchmark for assessing whether combining the two modalities would result in a meaningful therapeutic advantage. The researchers focused specifically on how the timing of cellular infusion after the initial radiation dose would influence the overall survival rate and the potential for long-term remission.
The data from the combination trials revealed a dramatic difference in outcomes that depended entirely on the radiation method employed. When CAR T cells were administered following conventional radiotherapy, the results were lackluster, with a median survival of only 37 days. This suggested that the traditional radiation field offered no real benefit to the subsequent immunotherapy. However, the group receiving the minibeam and CAR T cell combination saw survival times soar to a median of 83 days. This was the most successful outcome recorded in the study, representing a significant leap forward in therapeutic efficacy. Even more impressive was the fact that 25% of the animals in the minibeam combination group became long-term survivors, remaining disease-free beyond the 90-day mark. This synergy indicates that the spatial arrangement of the radiation beams plays a vital role in priming the tumor site for immune infiltration, effectively turning a hostile environment into a productive one.
Biological Context: Creating a Permissive Environment for Immunotherapy
The failure of conventional radiation to enhance CAR T cell performance appears to be rooted in the specific biological context it creates within the brain. Histopathological analysis of brains treated with the conventional combination showed evidence of diffuse tumor spread and significant tissue necrosis. Researchers observed that the simultaneous attack on the tumor by both high-dose uniform radiation and potent immune cells likely overwhelmed the brain’s innate waste-clearance systems. This created a toxic inflammatory environment that resulted in extensive damage to the surrounding healthy tissue, effectively sabotaging the recovery process. Instead of providing a clear path for the immunotherapy, the uniform radiation seemed to trigger a defensive, immunosuppressive response that limited the ability of the CAR T cells to hunt down residual malignant cells. This antagonistic relationship underscores the limitations of using old-world radiation techniques alongside modern bio-therapies.
In contrast, minibeam radiation therapy created what researchers described as a ‘permissive’ environment that actively supported the function of infused immune cells. Brains treated with the minibeam combination exhibited ‘structurally loose’ residual lesions with minimal vascular abnormalities and far less inflammatory infiltration compared to their conventional counterparts. By leaving the low-dose ‘valleys’ intact, MBRT avoids triggering the massive fibrotic response and immunosuppressive signaling pathways that typically follow uniform irradiation. This preservation of the microenvironment allows for better oxygenation and nutrient delivery, which are essential for the persistence and metabolic health of CAR T cells. Only 37.5% of the animals in the minibeam group had detectable residual tumors at the end of the observation period, suggesting that the spatial fractionation allowed the immunotherapy to complete the task of eradication that the radiation beams had started.
Optimization Strategies: Safety Profiles and Timing Considerations
Beyond its therapeutic efficacy, minibeam radiation therapy demonstrated a markedly superior safety profile that is critical for clinical translation. In the experimental groups, animals treated with conventional beams frequently developed visible skin injuries and significant hair loss at the radiation entry site, requiring topical medical intervention to manage the discomfort. Those in the minibeam group, however, displayed only minor and self-limiting skin reactions that did not interfere with their quality of life. More importantly, the internal imaging and post-mortem analysis showed a complete absence of the massive tissue necrosis that plagued the conventional combination group. This suggests that MBRT is a much safer partner for high-potency cellular therapies, as it does not push the brain beyond its physiological limits of recovery. Reducing these severe side effects is paramount for patients who are already weakened by the aggressive nature of lymphoma and the toxicity of prior chemotherapy.
The study further illuminated the critical role of timing when integrating radiation with cellular immunotherapy. Researchers compared the results of infusing CAR T cells three days versus five days after the completion of the minibeam treatment. While both groups showed some improvement, the five-day delay resulted in significantly better survival outcomes, with a median of 83 days compared to 35.5 days for the earlier infusion. This finding suggests that the brain requires a brief ‘recovery window’ to stabilize after the physical stress of radiation. Allowing a five-day gap likely gives the inflammatory markers a chance to subside and the local vasculature a moment to normalize, creating the optimal conditions for the CAR T cells to engraft and begin their work. This discovery highlights that the success of complex combination therapies depends not just on the tools used, but on the precise orchestration of each intervention to align with the body’s natural healing rhythms.
The Path Forward: Future Implications for Clinical Oncology
While the preclinical results provide a strong foundation for optimism, several limitations remain that will guide the next phase of research. The use of immunodeficient rat models was necessary to ensure the acceptance of human lymphoma and CAR T cells, but it means that the role of a fully functional, endogenous immune system has yet to be fully characterized. Additionally, the study was conducted exclusively on male animals and used a specific CAR T product that was predominantly CD4-positive, leaving questions about how different cell ratios or gender-specific biological factors might influence the outcome. There is also the possibility that some tumors identified as cleared had simply downregulated the target antigen rather than being completely eradicated. These variables represent the next frontier for researchers as they work to refine the protocol and ensure that the transition from the laboratory to the hospital is as safe and effective as possible for all patient demographics.
Medical professionals and researchers moved forward with these findings to establish a new paradigm for treating aggressive brain cancers. The study effectively demonstrated that the spatial modulation of radiation could solve the long-standing problem of therapeutic toxicity in neuro-oncology. Stakeholders began developing specialized collimators and delivery systems to bring minibeam technology into human clinical trials, focusing on patients who had exhausted traditional treatment options. These efforts prioritized the creation of standardized protocols that carefully balanced radiation peaks with the timing of cellular infusions to maximize the ‘permissive’ environment identified in the lab. Furthermore, the integration of real-time imaging helped clinicians monitor the ‘valley’ regions to ensure that the blood-brain barrier remained intact while the tumor was being targeted. This collaborative approach shifted the focus toward a more holistic strategy of microenvironmental management.